
Key Takeaways
- In laryngectomy the voice box (larynx) is removed and mostly it is done for laryngeal cancer.
- Partial laryngectomy takes out only the part with cancer and you usually keep your voice, but in total laryngectomy the whole voice box goes, and you breathe from a hole in the neck (stoma) for life.
- Hospital stay is mostly around 7 to 10 days and you take a few months to fully recover.
- Even after total laryngectomy, you can learn to speak again.
- Taking care of the stoma, wearing a stoma filter and getting thyroid tests done becomes part of your routine.
- Don’t stop thyroid tablets or any other medicine, and don’t skip follow up without asking your doctor.
- If you are unable to breathe from the stoma even after cleaning it or there is heavy bleeding from the neck, rush to the hospital emergency.
Voice box cancer is not rare in India. Laryngeal cancer alone is around 3 to 6% of all the cancers in men and in most of them it has already spread nearby by the time it is caught (Bobdey et al., 2015), so a lot of patients end up hearing the word ‘laryngectomy’ from their doctor.
When patients and families first hear this word they get shocked and scared, because they think it means they will never talk again. Actually it depends on whether you need partial or total laryngectomy, and even after total laryngectomy most people learn a new way of speaking and many of them go back to their work and normal family life.
In this blog we will tell you what laryngectomy is, what are the types of laryngectomy, how total and partial laryngectomy surgery is done, how the recovery goes, how to live with a stoma and how Dr. Amit Chakraborty can help you.
Has your doctor advised a laryngectomy?
What Is Laryngectomy?
Laryngectomy is surgery to remove your voice box (larynx), either partially or completely. The larynx sits in the front of the neck just above your windpipe and it has three jobs. Your voice comes from here, air passes from here to the lungs and when you swallow it shuts the airway so that the food goes down the right way and not into the lungs.
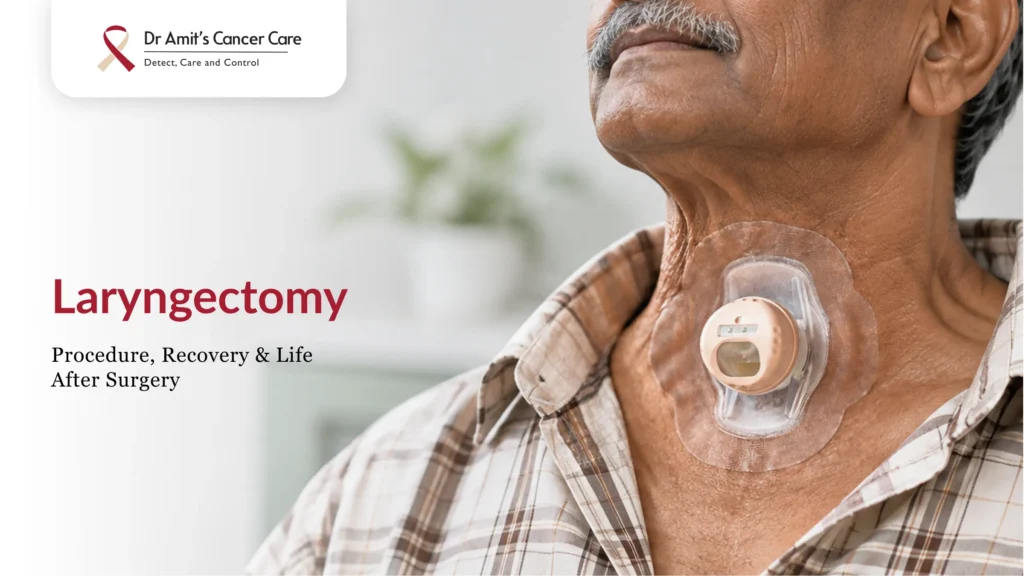
To understand it in simple terms, in a normal person the mouth, nose, food pipe and windpipe are all joined at the throat. In total laryngectomy the voice box is taken out and the windpipe is brought out and stitched to a small opening in front of the neck, which is called stoma. From now on you breathe in and out only from this opening and your mouth and nose only connect to the food pipe. So food and drink do not normally go into the lungs, but a leak around a voice prosthesis or an abnormal opening can still let liquids reach the airway. Air also stops passing through your mouth and nose.
Mostly laryngectomy is done for laryngeal cancer, which many times starts as a hoarseness of voice that just does not go away, and sometimes it is done for hypopharyngeal cancer where the lower throat around the voice box is also involved.
Why Is Laryngectomy Surgery Done?
A lot of patients with voice box cancer are first given radiation or chemo along with radiation to try and save the voice box, and a long-term study showed chemoradiation saved the voice box better than only radiation (Forastiere et al., 2013). But still in some cases laryngectomy has to be done. Following are the common reasons:
- Advanced cancer which has grown into the cartilage of the voice box
- Cancer which comes back after radiation or chemoradiation, and this is called salvage laryngectomy
- A voice box which is badly damaged and not working, so that food and water keep going into the lungs
- Early cancer in a small area, which can be removed with a partial laryngectomy instead of radiation
According to recent studies, total laryngectomy is mostly kept for advanced tumours that have gone into the cartilage, for cancers which come back after other treatment and for a voice box that is not working anymore (Thurnher et al., 2025). Your doctor will check the scope, scans, biopsy and then tell you which one is for you and explain all the surgical options for throat cancer.
Types of Laryngectomy
Which type of laryngectomy you get depends on where the cancer is and how much of the voice box it has covered. The table below explains the main types:
| Type | What is removed | What it usually means for you |
| Transoral laser surgery (cordectomy) | Part or all of one vocal cord, through the mouth | No cut on the neck, voice is kept but may be hoarse |
| Vertical partial laryngectomy (hemilaryngectomy) | One side of the voice box | Voice is weaker, you speak normally |
| Supraglottic laryngectomy | Upper part above the vocal cords | Voice stays, swallowing needs practice for few weeks |
| Supracricoid partial laryngectomy | Most of the voice box, keeping the base (cricoid) and at least one movable part | Rough voice, longer swallowing training, temporary tube in the neck |
| Total laryngectomy | Whole voice box | Permanent stoma, new way of speaking |
| Total laryngopharyngectomy | Voice box and part of the throat | Throat rebuilt with tissue from elsewhere, longer recovery |
Partial laryngectomy vs total laryngectomy
After partial laryngectomy some of your own voice mostly stays, and when the temporary tube in the neck (tracheostomy) comes out, you start breathing from your nose and mouth again. Still, it is not for everyone.
Open partial surgery mostly suits carefully selected people whose lungs and general health are good, with age considered alongside these factors, because some of the airway protection is lost and for a few weeks the lungs have to manage some coughing while you swallow (Thurnher et al., 2025).
With total laryngectomy the cancer is taken out fully in one surgery and the food pipe is separate from the airway, though swallowing problems can still happen. You also lose your own voice and breathe from the stoma for life.
Which option is better for you depends on the size and location of the cancer, your previous treatment, and your health, and it is completely fine to ask your doctor why they are suggesting one over the other.
How Is Laryngectomy Surgery Done?
Before the surgery
Before the surgery there will be blood tests, a CT or MRI scan and a check up of your heart and lungs. Stop smoking and drinking completely before this, as both of them make healing slow. In most hospitals you will also meet a speech therapist first, so you have an idea how you will talk after the surgery, and a dentist if any teeth need treatment.
During the surgery
The surgery is done under general anaesthesia and it takes a few hours. The surgeon takes out the voice box through a cut in front of the neck and makes the stoma. Sometimes the neck lymph nodes are also removed at the same time (neck dissection), and in some patients a small opening is made between the windpipe and food pipe for a voice prosthesis.
After the surgery
For the first day you may be kept in the ICU. There will be one or two drains in your neck, a feeding tube through your nose and a tube in the stoma, and you cannot eat from the mouth for some days till the throat heals.
Laryngectomy Recovery Timeline
Everyone recovers differently, and if you had radiation before the surgery it takes longer. A few simple tips for a smooth recovery after head and neck surgery help a lot at home. The table below shows what usually happens:
| Time after surgery | What you may notice |
| Day 1 to 3 | ICU or ward, drains in the neck, lot of mucus from the stoma which nurses clean often |
| Day 3 to 7 | Drains removed, walking around the ward, feeding only through the nose tube |
| Day 7 to 14 | Swallow test, then liquids and soft food if the throat has healed, family taught stoma care, discharge |
| Week 2 to 6 | Tiredness, neck stiffness and swelling, communication by writing or electrolarynx |
| Week 6 to 12 | Radiation in some patients, speech therapy, slowly back to light work |
| After 3 months | Most daily activities are back to normal and a new voice is improving |
These timelines are general so your doctor may change them as per your healing and other treatment.
Risks and Side Effects of Laryngectomy
Laryngectomy is a big surgery and like every surgery there are some risks. Following are the common ones:
- Pharyngocutaneous fistula, which means saliva leaks from the throat to the skin of the neck. One study on 422 patients saw it in around 21% after first surgery and around 33% when the surgery was done after radiation failed, and wound infection was the biggest risk factor (Šifrer et al., 2023). Some fistulas heal with wound care and temporary changes to feeding, while others need further treatment.
- Wound infection or bleeding
- Narrowing of the stoma or of the food pipe over time
- Low thyroid (hypothyroidism), which a review of 3,061 people found in about half the patients, more so when part of the thyroid was removed or radiation was given (Tan et al., 2026)
- Loss of smell and taste because air does not pass through the nose
- Feeling sad, worried or shy about the stoma and the new voice
Results from one hospital can be different from another, so ask your own doctor what your risk is. And if thyroid tablets are started, do not skip even a single day and get the thyroid test done on time.
| Expert Insight “Families usually ask me if life will ever feel normal after a total laryngectomy. What I always tell them is that the first few weeks are the hardest and then things slowly settle. Once the stoma care becomes a habit and the speech therapy starts, most patients are back to eating at the family table, going out and talking with their loved ones again.” Dr. Amit Chakraborty MBBS, MS, MCh (Surgical Oncology), MRCS (UK) Head & Neck Cancer Specialist Registered Medical Practitioner | 2008113798 |
Living With a Stoma After Total Laryngectomy
Normally your nose warms the air, makes it moist and filters it before it goes to the lungs. After total laryngectomy the air goes straight in from the stoma, so you have to take care of the stoma every day. Following are a few things that help:
| Wipe the mucus around the stoma few times a day with a wet cloth or gauze, the way your nurse showed you. Use a stoma filter, also called as heat and moisture exchanger (HME). In a randomised study on 80 people, the ones who used an HME had a lot less cough and did not need to clean the stoma so often (Bień et al., 2010). Keep drinking enough water and use a humidifier or the saline nebuliser advised by your care team when the air is dry. If they recommend steam, avoid boiling water. Keep away from dust, kitchen smoke from tadka, agarbatti, mosquito coil and Diwali crackers, and when you step out cover the stoma with a cloth or filter. While bathing use a suitable shower guard if advised, and keep shower or mug water below the stoma. Do not let water enter the opening. Never go for swimming or into deep water, as water going into the stoma goes straight into the lungs. Keep a card or band which says you are a neck breather, because in an emergency oxygen and breathing support has to be given to the neck and not the mouth. |
Speaking After Laryngectomy
After partial laryngectomy most people talk in their own voice, though it can be rough or weak. After total laryngectomy you will need a new way to talk, and the three main options for speaking after laryngectomy are an electrolarynx, a voice prosthesis and oesophageal speech. Your family plays a big role here, because with their patience and practice at home the new voice gets better with time.
When to Call Your Doctor After Laryngectomy
| When to Get Medical Advice Call your doctor if you get fever, redness or swelling around the wound, saliva or fluid leaking from the neck, food coming out of the stoma or the stoma looking smaller than before. Also tell the doctor if you feel very tired, cold all the time or you are gaining weight, as it can be low thyroid. If you are not able to breathe from the stoma even after cleaning it or there is heavy bleeding, go to the hospital emergency at once and tell them you are a neck breather. |
Dr. Amit Chakraborty, Head & Neck Cancer Specialist (MBBS, MS, MCh Surgical Oncology, Registered Medical Practitioner: 2008113798), says that whether a patient needs partial or total laryngectomy is decided only after going through the scope findings, scans and the treatment taken before, so that voice and swallowing are saved as much as safely possible. If you have been told to get a laryngectomy and want to be sure, you can take a second opinion or know more about laryngeal cancer treatment with Dr. Amit.
Have a question about neck dissection surgery?
This article is for general health education and is not a substitute for personal medical advice. Please speak to your treating doctor about your own surgery and recovery plan.
References
- Bień, S., Okła, S., van As-Brooks, C.J., et al. (2010). The effect of a heat and moisture exchanger (Provox HME) on pulmonary protection after total laryngectomy: a randomized controlled study. European Archives of Oto-Rhino-Laryngology, 267(3), 429-435.
- Bobdey, S., Jain, A. and Balasubramanium, G. (2015). Epidemiological review of laryngeal cancer: An Indian perspective. Indian Journal of Medical and Paediatric Oncology, 36(3), 154-160.
- Forastiere, A.A., Zhang, Q., Weber, R.S., et al. (2013). Long-term results of RTOG 91-11: a comparison of three nonsurgical treatment strategies to preserve the larynx in patients with locally advanced larynx cancer. Journal of Clinical Oncology, 31(7), 845-852.
- Šifrer, R., Strojan, P., Tancer, I., et al. (2023). The incidence and the risk factors for pharyngocutaneous fistula following primary and salvage total laryngectomy. Cancers, 15(8), 2246.
- Tan, J.Y., Westwood, E. and Edafe, O. (2026). Incidence, risk factors and prevention of hypothyroidism following laryngectomy: a systematic review and meta-analysis. Annals of the Royal College of Surgeons of England, 108(3), pp. 161–169. doi:10.1308/rcsann.2025.0001.
- Thurnher, D., Simo, R., Succo, G., Vilaseca, I. and Simon, C. (2025). Open partial or transoral laryngectomy, total laryngectomy today. Frontiers in Oncology, 15, 1520524.


 Jun 16, 2025